Tuesday, October 25, 2011

Normal Variant: Cervical Rib


Note the corresponding transverse process points caudally => Cervical origin
Incidental finding of Cervical rib.
Can be unilateral or bilateral.
0.5 - 8% of population*
Usually asymptomatic, but occasionally may give rise to complications.
Think about the anatomical structures that goes through the thoracic outlet, and the attachment of the scalene muscle.

Complications:
- Usually in adulthood
- Thoracic outlet syndrome
- Subclavian artery aneurysm as a result of compression

DDx:
- Hypoplastic 1st rib (rudimentary 1st rib)
- Elongated transverse process of C7

Key to differentiate from the other DDx:
(1) Check transverse process. Cervical transverse process points down, 1st thoracic transverse process points up.
(2) Check presence of joint space between the rib and the transverse process. Absent joint space means it's a elongated transverse process.

Right cervical rib. Note the transverse process pointing down.


*Reference from: Guttentag AR, Salwen JK. Keep your eyes on the ribs: the spectrum of normal variants and diseases that involve the ribs. RadioGraphics 1999;19:1125-1142

Wednesday, October 5, 2011

Case: Aortic Dissection and its classification


 Classification for Aortic Dissection


DeBakey
Stanford


I
A (60%)
Involves both Ascending and Descending aorta


Intimal flap present in both ascending (small circle) and descending (large circle) aorta.
Same patient on Coronal view. Note the peri-aorta haematoma (pink arrow)


II
Involves the Ascending aorta, up to the aortic arch


Intimal flap present only in the ascending aorta.
Same patient in Coronal view.
Intimal flap in Ascending aorta.
Intimal flaps. Don't mistake the aortic valves for intimal flap.

III
B(40%)
Involves the Descending aorta only.


Involves the Descending aorta only. Note the beak sign (arrow), which signifies the false lumen.
Same patient in Pre-contrast phase.


Note: DeBakey system is less commonly used now.

How I remember DeBakey system: 
Type I for ONE whole stretch (from ascending to descending), the rest of the types are A and B.


How I remember Stanford's classification:
Type A for Ascending, Type B for Below.

Landmark: 
- Left subclavian artery: Distal to this = Descending artery

Important remarks in a report: *remember to evaluate the whole aorta from top down*

  • Stanford type A (surgical management) or B (non-surgical management)
  • Rupture or not? Presence of haemothorax is a quick and easy sign
  • Origin and extent of the dissection
  • Presence of aneurysm / Diameter of the aorta
  • Identify the false and true lumen (important in interventional management) - this can be identified by tracing the dissection to the end, delayed enhancement in the false lumen
  • Identify the complications:
    • Involvement of the important arteries: coronary arteries, common carotid arteries, iliac arteries
    • Involvement of end organs eg kidneys, intestines, resulting in ischemia / infarction (this is an indication for surgical management)
    • Cardiac tamponade as a result of bleed into the pericardium
    • Heart failure
  • Identify presence of haematoma in the mediastinum, pleura, pericardial or aorta

Associated conditions:

  • Connective tissue disorder: Marfan syndrome, Ehlers-Danlos syndrome
  • Turner syndrome
  • Conditions where the aorta is subjected to high pressure:
    • Hypertension
    • Aortic coarctation
    • Aortic stenosis, Bicuspid aortic valve
    • Pregnancy
  • Cystic medial necrosis


Differential diagnosis:
- Penetrating atherosclerotic ulcer
- Intramural haematoma (IMH) - also a form of aortic dissection, but without breaching the intima
- Pseudodissection as a result of motion artifact on CT scanning

In any case, remember to pick up the phone and call the surgeons! Happy reporting.

Friday, September 30, 2011

Normal Variants: Paranasal Sinuses

Normal variants in the paranasal sinuses

Note listed are only the more common ones.
These are important in radiology report, as gives the endoscopist an idea what to look out for (Surgical planning).


Name
Location
Implication


Agger nasi cell
Ethmoid aircells. Located most anteriorly, infront of the cribriform plate where the middle turbinate attaches

If inflamed, patient may experience epiphora as it is close to the medial canthus

Agger nasi cell on the left side, just inferior to the frontal sinus


Haller cell
(MaxilloEthmoidal cell, Infraorbital cell)
Aircells located along the margin of the orbital floor. Inferolateral to the ethmoidal bulla.

Presence of these cells may narrow the infundibulum and/or maxillary sinus ostium. Prone to obstruction and inflammation of the maxillary sinus.


Large right Haller cell


Onodi cell
Ethmoid aircells that extends into the sphenoid bone, located superior to the sphenoid sinus.

At risk of intracranial extension of the endoscope if surgeon (endoscopist) is not aware of the presence of Onodi cell.


Concha bullosa
Pneumatized middle turbinate. These cells usually communicates with the anterior ethmoid aircells.

Large concha bullosa enlarges the turbinate,  makes one prone to obstruction/ inflammation.

Concha bullosa also makes endoscopic access more difficult.


Right concha bullosa. Notice the right middle turbinate is larger than the left (with absence of concha bullosa).


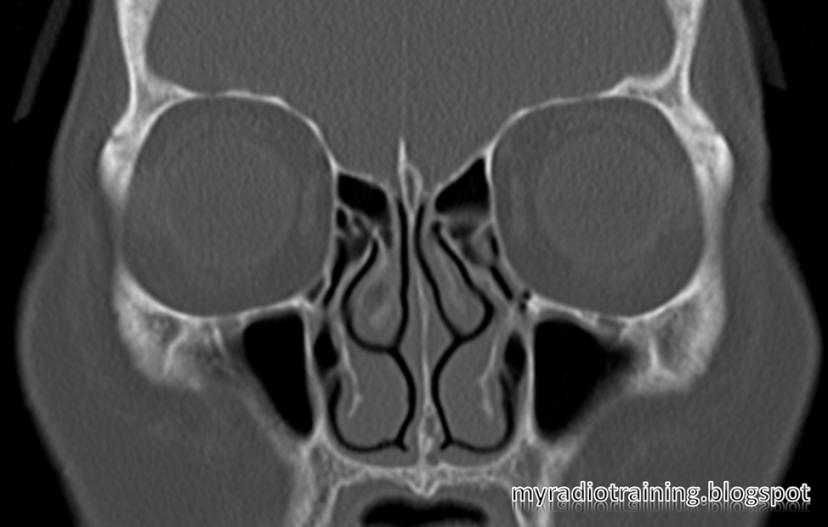
What normal variant(s) did you see here?


Saupe Classification


Saupe's Classification: Based on the position of the accessory ossification center

More about bipartite patella here


Type I (5%)
Accessory ossification center at the inferior pole

Type II (20%)
Accessory ossification center at the lateral margin


Type III (75%)
Accessory ossification center at the superolateral pole

Normal Variant: Bipartite Patella

Bipartite patella occurs due to presence of unfused ossification centre.
Other variants include

  • Tripartite patella
  • Multipartite patella
These normal variants can be classified using Saupe's classification.

Male : Female = 9 : 1
Occurs in 2% of population
Usually asymptomatic

Saupe type 3 Bipartite patella. About half of bipartite patellae are bilateral.

Ossification:
  • Primary ossification begins at 5 - 6 years old
    • 77% from one center
    • 23% from two or three centers
    • The ossification centers usually fuse mutually


Wednesday, September 21, 2011

Keros Classification


Keros Classification in CT scan of the paranasal sinuses

Measures depth of the olfactory fossa

Measurement:
Distance from the lamina cribrosa to the roof of ethmoid (highest point)


Note:
Depth of the olfactory fossa can be asymmetrical

Note the measurement (double-head arrow)


Keros type
Measurement
Illustration
1
1-3 mm
Keros type 1: notice relatively shallow olfactory fossa

2
4-7 mm

Keros type 2: Deeper olfactory fossa


3
8-16 mm
Keros type 3: Deep olfactory fossa


Implication:
Stratifies the risk of intracranial penetration during ENT surgery


Monday, September 19, 2011

Proximal tibial fracture - Schatzker Classification


Schatzker Classification for Fracture of the proximal tibia / tibial plateau

Type 1
Vertical split of the lateral condyle


Type 2
Vertical split of the lateral condyle  + compression fracture of the adjacent weight bearing lateral condyle;
Associated with Fibular head/neck fracture

Schatzker 2: Vertical split of lateral condyle. There was no fibula fracture in this case.

Schatzker 2: Same patient on CT scan


Type 3
Intact condylar margin, but depressed lateral tibial plateau articular surface


Type 4
Medial condylar fracture
Schatzker 4: High energy type, where there is also involvement of the intercondylar eminence

High energy type: + involvement of intercondylar eminence
Low energy type: crush fracture of the medial tibial plateau (irreconstructible)

Type 5
Bicondylar fracture, tibial shaft act as a wedge in between

Schatzker 5: Bicondylar fracture. Notice an inverted 'Y' appearance?

Type 6
Condylar fracture + Shaft fracture (metaphysis disconnected from diaphysis)
Schatzker 6: Bicondylar fracture and...
Schatzker 6: and tibial shaft fracture.  From the same patient.